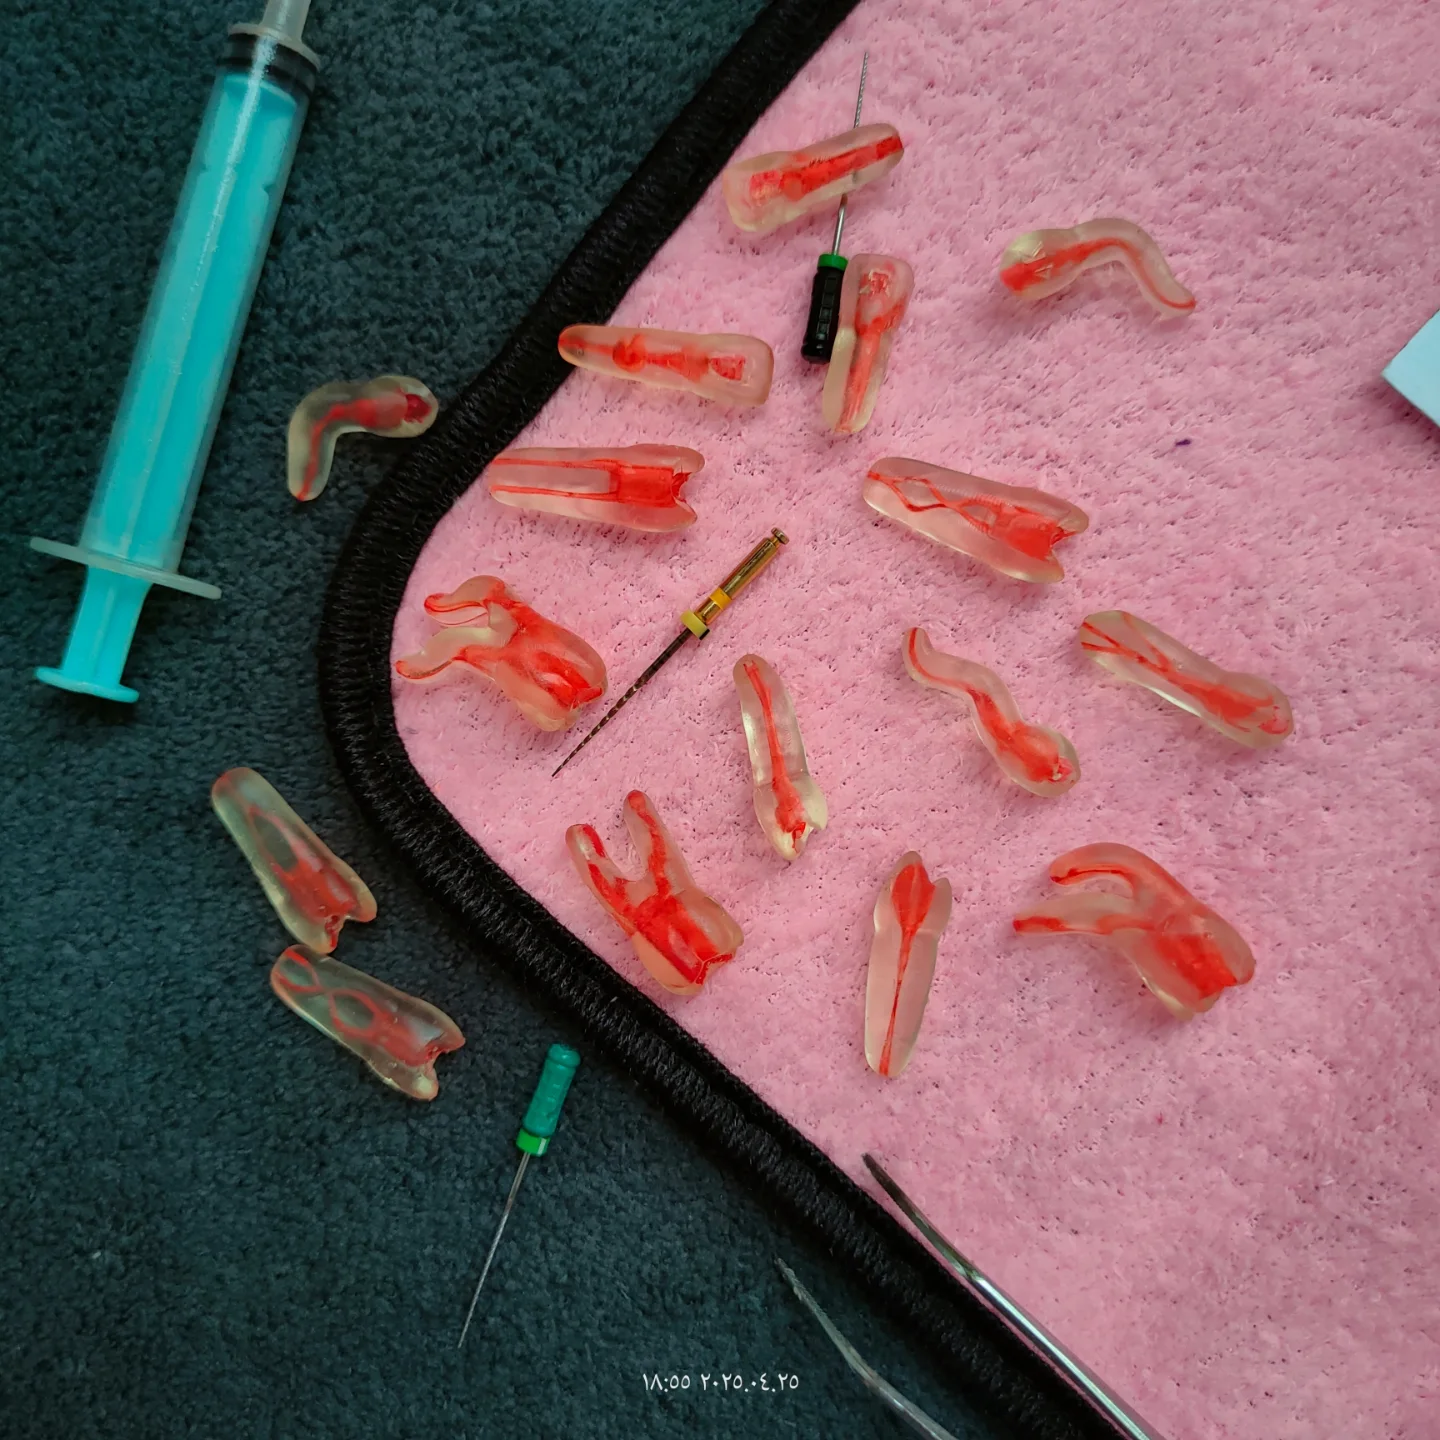
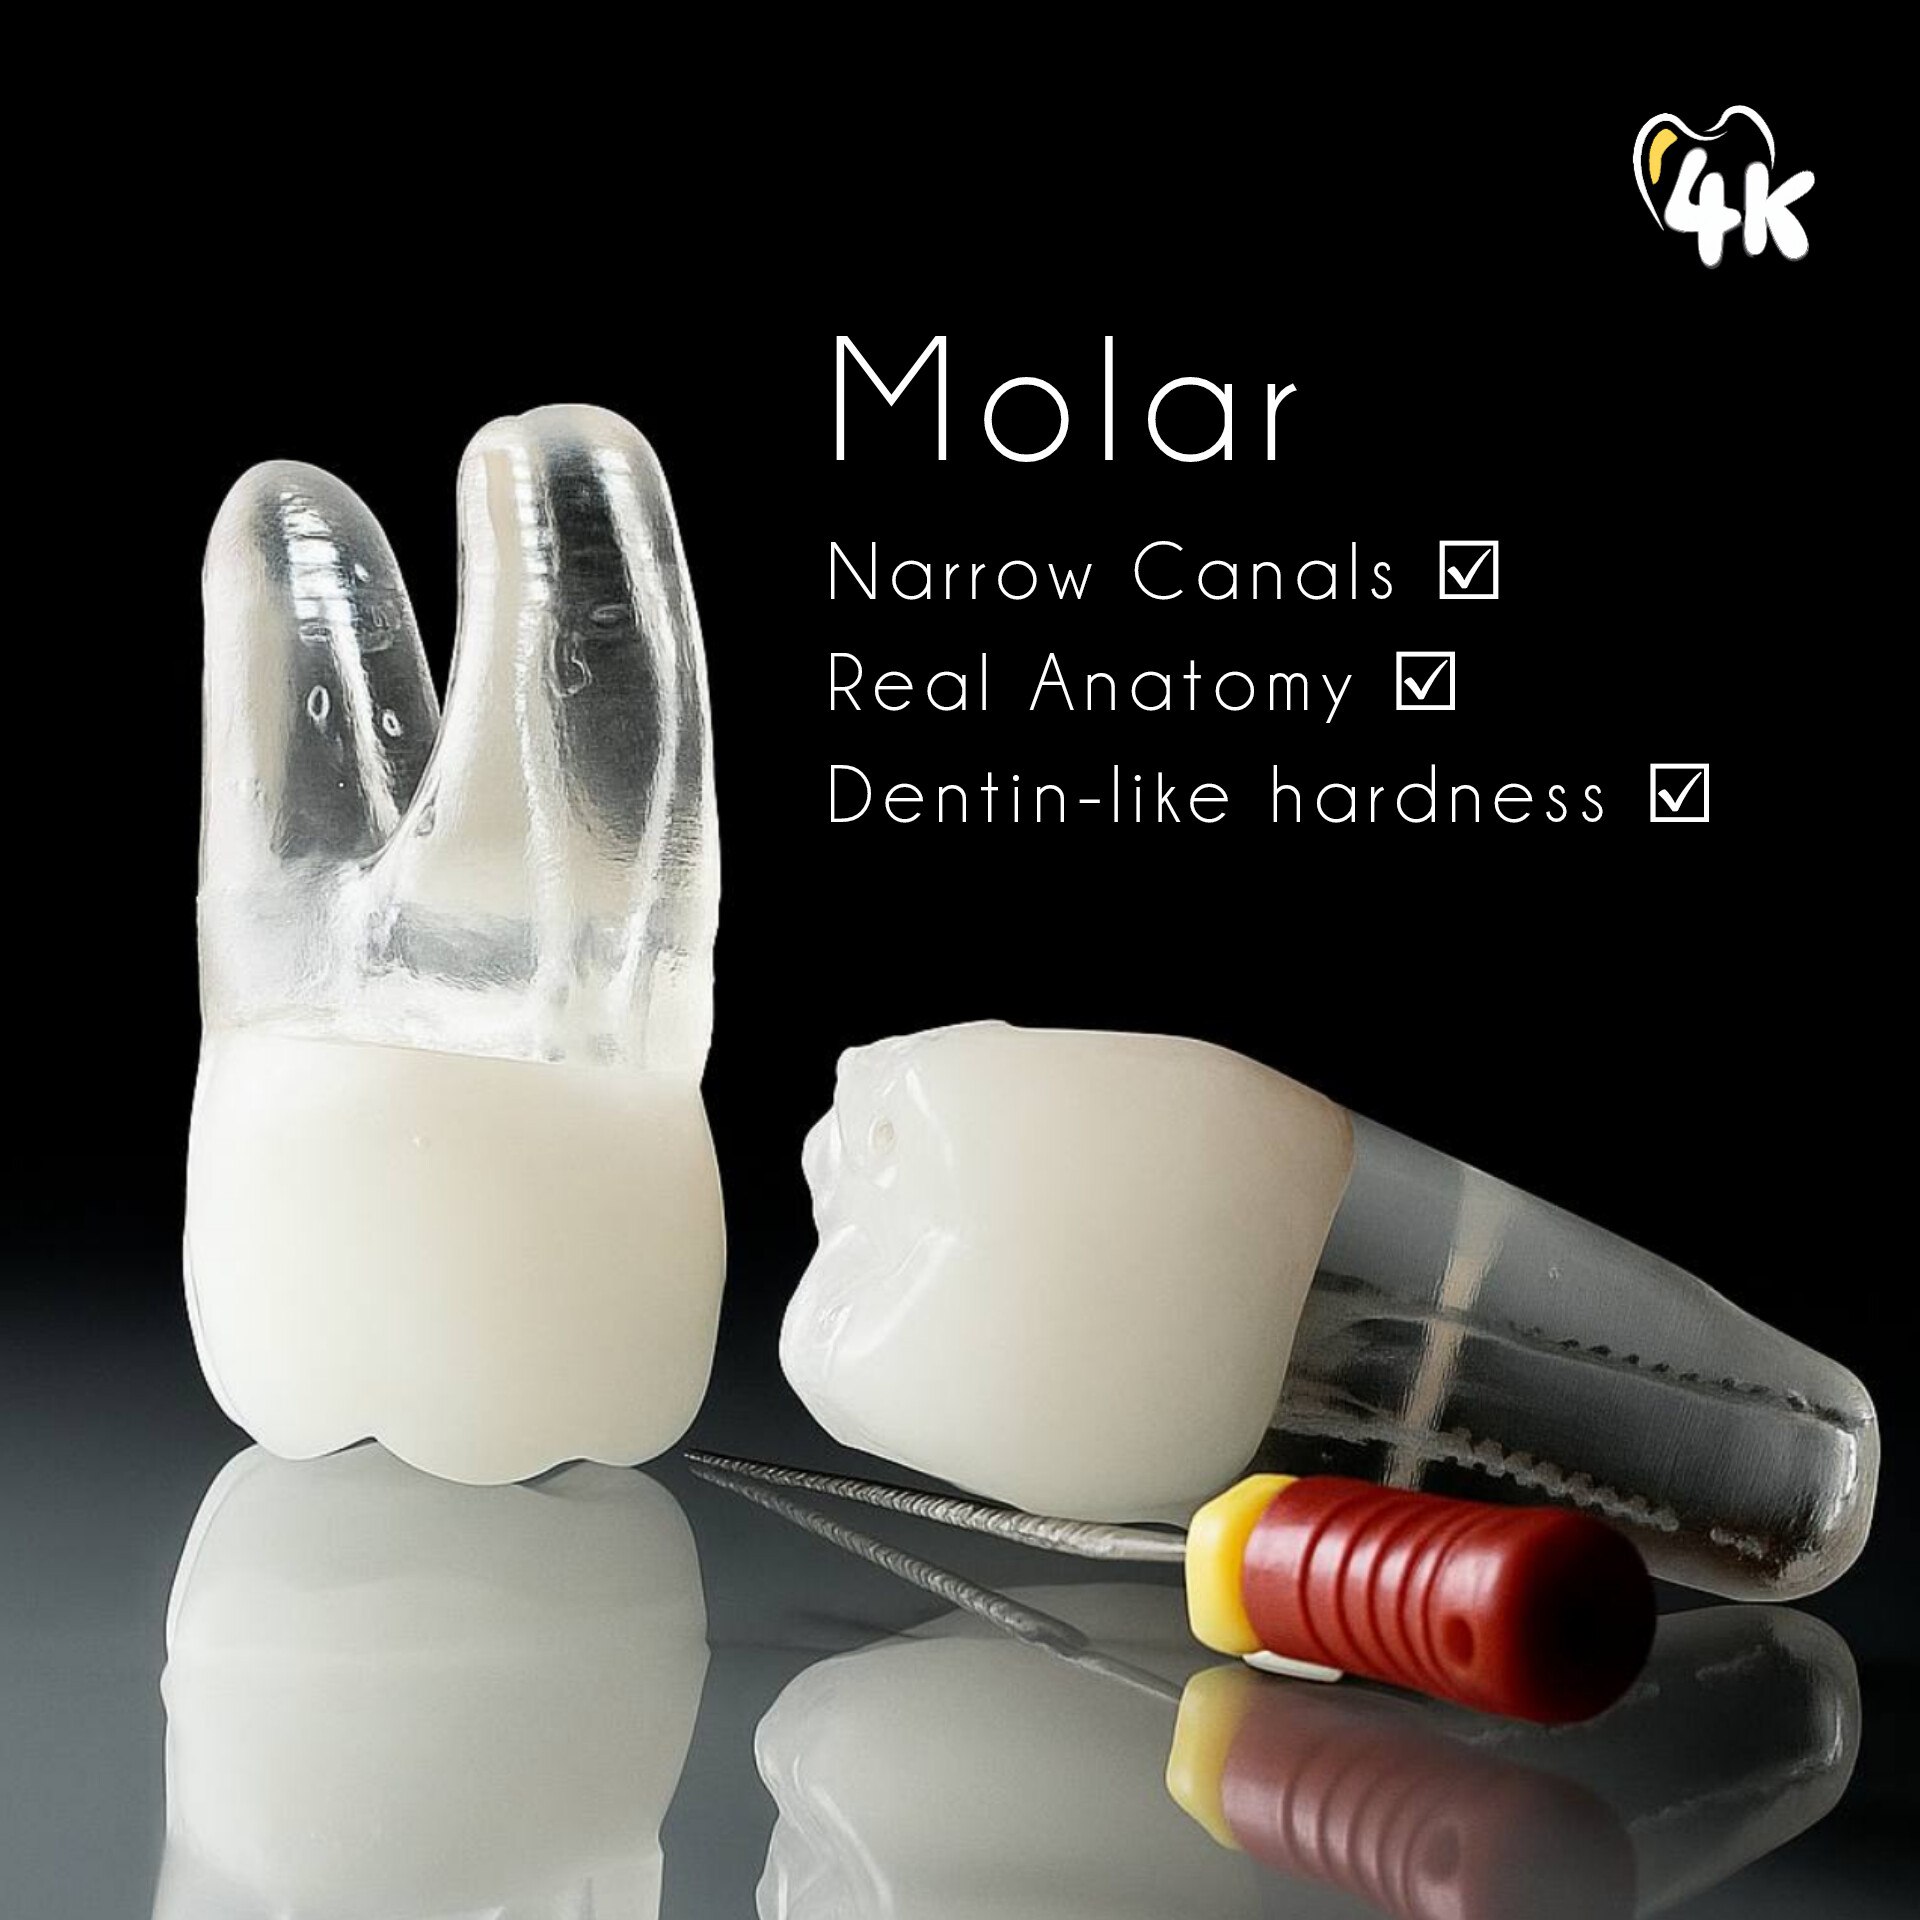
"34-micron resolution" looks good on a product page. But resolution alone does not make a training model — plenty of high-resolution prints teach the wrong thing because nobody checked how they feel under a file. What makes a 4K model usable is not a single number; it is a loop. Here is how a model actually gets made.
1. Start from real anatomy
A useful training tooth begins as a real one. We work from anatomical data — CT and micro-CT references — so the canal system a student negotiates is a faithful version of something that exists in a mouth, not an idealised diagram. The morphology that makes a case difficult clinically is the morphology we want on the bench.
2. Design the challenge, not just the shape
A scan gives you geometry. It does not give you a lesson. The design step is where a model becomes teaching tool: we decide which clinical challenge this unit isolates — a separated file 3 mm from the apex, an MB2 that is genuinely hidden, an S-curve that loads the file against the outer wall — and we shape the model so that challenge is unavoidable and repeatable.
3. Print with SLA, tuned for feel
We print on stereolithography at 34-micron layer resolution. But the resolution is in service of the material behaviour, not the other way around. The goal is a print that reproduces a usable resistance profile: progressive feedback from orifice to apex, a detectable difference between patency and blockage, realistic loading on a curve.
Resolution is what a model is printed at. Feel is what it is judged by.
4. Bench-check on a clinician's hands
This is the step most catalogs skip. Before a model design ships, a clinician runs instruments through it the way they would in a patient — not to photograph it, but to answer one question: does a file behave in here the way a file behaves in a real canal? If the answer is no, the design goes back. A model that looks perfect and feels wrong fails the only test that matters.
5. Reproduce consistently
A training model is only useful if every unit in a cohort behaves the same. Twenty students working the same exercise should meet the same canal. Consistent production — same geometry, same material behaviour, unit after unit — is what lets an instructor grade fairly and debrief meaningfully.
Why the loop matters more than the spec
You can buy a high-resolution print anywhere. What is harder to find is a model where a dentist has already asked, on your behalf, whether it teaches the right reflex. That is the entire point of designing in Cairo, by a clinician, with the printer and the bench in the same workflow: the person who knows what a real canal feels like is the same person signing off the model.
See how each model maps to a clinical skill, or read why tactile feedback decides whether a model teaches.